
approach to right sided dilated heart by fetal echocardiography step by step;
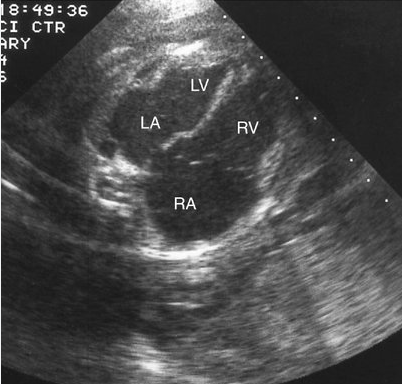
## 1. First confirm that the right heart is truly dilated
### Four-chamber view
Assess:
* RA size versus LA
* RV size versus LV
* RV/LV basal diameter ratio
* RV area versus LV area
* Apical position and morphology
* Ventricular function
* Interventricular septal configuration
* RA/RV hypertrophy
* Pericardial effusion
Remember that **mild right-sided dominance is physiologic in the fetus**, but significant asymmetry or progressive enlargement requires investigation.
### Important distinction
**RV dominance ≠ RV dilatation.**
A fetus may have a relatively larger RV because of normal fetal circulation. True pathological dilatation should be supported by quantitative measurements/Z-scores and associated Doppler or structural abnormalities.
---
# 2. Determine whether RA, RV, PA or all three are enlarged
This immediately narrows the differential.
| Finding | Important possibilities |
| ------------------------------------- | ------------------------------------------------------------------------------------------------------------------------------------------------ |
| RA + RV dilated | TR, Ebstein anomaly, pulmonary venous abnormality, TAPVC, AVSD, volume overload |
| RV + PA dilated | Increased pulmonary blood flow, pulmonary regurgitation, distal pulmonary obstruction with post-stenotic dilatation, some vascular abnormalities |
| RA + RV + PA dilated | Significant right-sided volume load, TAPVC/PAPVC, severe TR, high-output state |
| RA predominantly dilated | Significant TR, abnormal venous return |
| RV predominantly dilated | Volume overload, pulmonary regurgitation, altered ventricular loading |
| RV hypertrophy rather than dilatation | Pressure overload |
| RV dilated + LV small | LV obstruction/hypoplasia, coarctation spectrum, mitral/aortic stenosis, unbalanced AVSD |
---
# 3. Step-by-step fetal echocardiographic approach
## STEP 1 — Confirm situs and cardiac position
Check:
* Situs solitus/inversus
* Cardiac axis
* Levocardia/dextrocardia
* Abdominal situs
* IVC and descending aorta relationship
Abnormal situs should immediately increase suspicion for:
* TAPVC
* systemic venous anomalies
* heterotaxy
* interrupted IVC
* anomalous pulmonary venous drainage
* complex CHD
---
# STEP 2 — Examine the systemic veins
### IVC
Look for:
* Normal IVC → RA connection
* Interrupted IVC
* Enlarged azygos
* Abnormal systemic venous drainage
### SVC
Check:
* SVC size
* Bilateral SVC
* Persistent left SVC
* Abnormal venous connections
Systemic venous anomalies alone don't necessarily cause marked RA/RV dilatation, but they may provide an important clue to **heterotaxy/complex venous anatomy**.
---
# STEP 3 — Examine the tricuspid valve carefully
This is one of the most important steps.
Assess:
* Valve morphology
* Leaflet displacement
* Coaptation
* Annular size
* TR
* TR velocity
* TR jet direction
* RA enlargement
* RV enlargement
* RV function
### Major differential: Ebstein anomaly
Look for:
* Apical displacement of septal/posterior tricuspid leaflet
* Large RA
* Atrialized RV
* Functional small RV
* Significant TR
* Cardiomegaly
* Possible pulmonary hypoplasia
Severe Ebstein anomaly can produce **massive RA enlargement with functional RV abnormalities**.
---
# STEP 4 — Assess tricuspid regurgitation
If TR is present, determine severity.
### Mild TR
May be transient/physiologic.
### Moderate/severe TR
Look for:
* RA enlargement
* RV enlargement
* Cardiomegaly
* Hepatic vein pulsatility/reversal
* Abnormal ductus venosus flow
* Pericardial effusion
* Hydrops
Differential includes:
* Ebstein anomaly
* tricuspid dysplasia
* pulmonary atresia/intact septum
* severe pulmonary stenosis
* AVSD
* arrhythmia
* fetal anemia/high-output state
* myocardial dysfunction
---
# STEP 5 — Examine the pulmonary valve and pulmonary artery
Assess:
### Pulmonary valve
* Morphology
* Opening
* Peak velocity
* Stenosis
* Regurgitation
### Main PA
Measure:
* Main PA diameter
* RPA/LPA
* PA/Ao relationship
### Important differential
If **PA is dilated**, consider:
* Increased pulmonary blood flow
* Pulmonary regurgitation
* Pulmonary valve abnormality
* Post-stenotic dilatation
* High-output circulation
* Abnormal pulmonary vascular anatomy
If **PA is small**, think more about:
* Pulmonary stenosis
* Pulmonary atresia
* TOF spectrum
* severe RV outflow obstruction
---
# STEP 6 — Examine the pulmonary veins very carefully
This is essential when you find unexplained **RA + RV dilatation**.
Identify all four pulmonary veins if technically possible:
* Right upper
* Right lower
* Left upper
* Left lower
Confirm:
**Pulmonary vein → LA drainage**
Look for:
* Absent/poor visualization
* Abnormal connection to systemic veins
* Vertical vein
* Dilated confluence
* Abnormal flow
* Pulmonary venous obstruction
### TAPVC
Particularly consider TAPVC when there is:
* RA enlargement
* RV enlargement
* PA enlargement
* Relatively small LA/LV
* Increased pulmonary venous flow to systemic venous circulation
* Abnormal pulmonary venous confluence
* Vertical vein or other anomalous drainage
A major point:
> **An unexplained enlarged right heart should trigger deliberate pulmonary-vein assessment.**
---
# STEP 7 — Look specifically for PAPVC
Partial anomalous pulmonary venous connection can be difficult to diagnose prenatally.
Suspect it when:
* Right heart is enlarged
* RA/RV volume overload is present
* No obvious intracardiac defect explains it
* Pulmonary veins cannot all be demonstrated entering LA normally
However, **PAPVC is considerably more difficult to establish confidently in the fetus than TAPVC**, and isolated PAPVC may be subtle.
---
# STEP 8 — Examine the atrial septum
Assess:
* Foramen ovale size
* Direction of flow
* Atrial septal aneurysm
* Restriction
* Abnormal atrial flow
Normally:
**RA → LA through foramen ovale**
If there is abnormal atrial flow or restriction, determine whether it contributes to right-sided volume/pressure changes.
---
# STEP 9 — Examine the ventricular septum
Look for:
* VSD
* AVSD
* Malalignment VSD
* DORV
* TOF
* ventricular disproportion
A large VSD generally does **not** produce dramatic fetal right-sided volume overload because pulmonary vascular resistance is high in fetal life. Therefore, marked fetal RA/RV enlargement should not automatically be attributed to a VSD.
---
# STEP 10 — Examine the mitral and aortic pathways
This is critical because a **small left heart can make the right heart appear disproportionately large**.
Assess:
### Mitral valve
* Size
* Stenosis
* Atresia
### LV
* Size
* Function
* Endocardial fibroelastosis
### Aortic valve
* Stenosis
* Atresia
* Flow
### Aortic arch
* Diameter
* Isthmus
* Flow
* Posterior shelf
* Arch hypoplasia
### Differential
* HLHS spectrum
* severe mitral stenosis
* aortic stenosis
* evolving HLHS
* coarctation of aorta
* LV dysfunction
---
# 4. Look for pressure overload versus volume overload
This distinction is extremely useful.
## A. Volume overload
Typically:
**RA/RV dilatation ± PA dilatation**
Consider:
* TAPVC
* PAPVC
* significant TR
* AVSD
* pulmonary regurgitation
* high-output state
The RV tends to be **dilated**, with increased volume loading.
---
## B. Pressure overload
Look for:
* RV hypertrophy
* increased TR velocity
* abnormal septal configuration
* reduced/absent pulmonary flow
* ductal flow abnormalities
Consider:
* severe pulmonary stenosis
* pulmonary atresia
* pulmonary hypertension
* ductal constriction/closure
* severe lung pathology
---
# 5. Always examine the ductus arteriosus
Measure:
* Ductus diameter
* Flow velocity
* Direction
* Pulsatility
* Diastolic flow
### Ductal constriction
Can produce:
**↑ RV afterload → RV pressure overload → TR → RV dysfunction**
Look for:
* increased ductal velocity
* turbulent flow
* reduced ductal diameter
* increased RV pressure
* TR
* RV hypertrophy/dysfunction
This is particularly important in a fetus exposed to **NSAIDs or other prostaglandin-inhibiting drugs**.
---
# 6. Evaluate the aortic arch and systemic output
A fetus with suspected:
* Coarctation
* LV outflow obstruction
* HLHS spectrum
may demonstrate:
**RV dominance + relatively small LV**
But this should be distinguished from true RV volume overload.
Assess:
* LV size
* mitral valve
* aortic valve
* ascending aorta
* transverse arch
* isthmus
* ductal arch
* flow direction
---
# 7. Search for high-output states
If there is marked right-heart enlargement, particularly with cardiomegaly, ask:
### Is there excessive venous return?
Consider:
* fetal anemia
* placental chorioangioma
* large AV malformation
* twin-twin transfusion
* sacrococcygeal teratoma
* fetal tumors
* severe hepatic vascular shunts
Look for:
* cardiomegaly
* increased cardiac output
* hyperdynamic ventricles
* abnormal venous Doppler
* MCA-PSV elevation
* hydrops
---
# 8. Examine rhythm
An arrhythmia can produce major right-sided changes.
Check:
* atrial rate
* ventricular rate
* AV relationship
* 1:1 conduction
* rhythm regularity
Consider:
* SVT
* atrial flutter
* ectopic atrial rhythm
* complete heart block
Persistent tachyarrhythmia can cause:
**TR → RA/RV enlargement → ventricular dysfunction → hydrops.**
---
# 9. Doppler assessment
I would routinely include:
### Venous Doppler
* Ductus venosus
* Umbilical vein
* IVC
* Hepatic veins if indicated
### AV valve Doppler
* Tricuspid inflow
* Mitral inflow
* TR
### Outflow
* Pulmonary valve
* Aortic valve
### Ductus arteriosus
* Peak systolic velocity
* Diastolic velocity
* Pulsatility
### Umbilical artery
Assess placental resistance.
### MCA
Especially if anemia/high-output state is suspected.
---
# 10. Differential diagnosis — practical classification
### **RA + RV dilatation**
Think first of:
1. **Significant TR**
2. **Ebstein anomaly**
3. **Tricuspid dysplasia**
4. **TAPVC**
5. **PAPVC**
6. **AVSD**
7. **Pulmonary regurgitation**
8. **High-output state**
9. **Tachyarrhythmia**
10. **LV hypoplasia/obstruction causing ventricular disproportion**
### **RA + RV + PA dilatation**
Particularly consider:
* TAPVC
* PAPVC
* significant TR
* pulmonary regurgitation
* increased pulmonary blood flow
* high-output circulation
### **RV dilatation + PA dilatation but no significant TR**
Consider:
* pulmonary volume overload
* pulmonary regurgitation
* anomalous pulmonary venous return
* high-output circulation
* vascular malformation
### **RV dominance + small LV**
Think:
* HLHS spectrum
* severe AS
* MS
* coarctation
* unbalanced AVSD
* LV dysfunction
---
# 11. My practical "5-question" approach
When you see fetal right-sided dilatation, ask:
**1. Is the RV truly dilated or simply dominant?**
↓
**2. Is this VOLUME overload or PRESSURE overload?**
↓
**3. Where is the extra blood coming from?**
* Pulmonary veins?
* TR?
* AVSD?
* High-output lesion?
↓
**4. Is the RV facing increased resistance?**
* Pulmonary stenosis?
* Ductal constriction?
* Pulmonary hypertension?
↓
**5. Is the left heart actually abnormal/small?**
* HLHS spectrum?
* AS/MS?
* Coarctation?
* LV dysfunction?
This approach prevents missing **TAPVC/PAPVC, Ebstein anomaly and evolving left-sided obstruction**.
---
# Suggested fetal echocardiography summary report
## FETAL ECHOCARDIOGRAPHY — SUMMARY REPORT
**Indication:** Fetal right-sided chamber dilatation.
### Cardiac position and situs
Situs solitus with levocardia. Cardiac axis is within normal limits.
### Four-chamber view
There is **[mild/moderate/severe] dilatation of the right atrium and right ventricle**, with **[normal/increased] RV/LV size ratio**. RV systolic function is **[normal/reduced]**. LV size and systolic function are **[normal/abnormal]**. No significant pericardial effusion.
### Atrioventricular valves
Tricuspid valve morphology is **[normal/abnormal]**. Tricuspid regurgitation is **[absent/mild/moderate/severe]**. Mitral valve morphology and function are normal. No significant AV-valve stenosis. No definite evidence of Ebstein-type apical displacement.
### Ventricular septum
No significant ventricular septal defect is identified on the present examination.
### Outflow tracts
LVOT and RVOT are normally related. Aortic valve is normal. Pulmonary valve is **[normal/stenotic/regurgitant]**. Main pulmonary artery is **[normal/mildly/moderately] dilated**.
### Pulmonary veins
Pulmonary venous drainage has been assessed. **[All visualized pulmonary veins appear to drain normally into the left atrium / abnormal pulmonary venous drainage is suspected / complete visualization is limited].** No definite evidence of TAPVC is identified on the present study.
### Systemic veins
IVC and SVC drain normally to the right atrium. No significant systemic venous anomaly identified.
### Aortic arch and ductus arteriosus
Aortic arch is **[normal/suspicious for hypoplasia/coarctation]**. Ductus arteriosus is patent. Ductal flow is **[normal / increased velocity with features suggestive of constriction]**.
### Interatrial septum
Foramen ovale is patent with predominantly right-to-left flow, appropriate for fetal circulation. No evidence of significant restriction.
### Doppler
Ductus venosus flow is normal. Umbilical artery Doppler is normal. MCA Doppler is **[normal / suggestive of increased peak systolic velocity]** where assessed. No significant abnormal venous flow.
### Rhythm and function
Regular fetal cardiac rhythm with heart rate of approximately **___ bpm**. No sustained tachyarrhythmia or bradyarrhythmia. Global cardiac function is preserved.
## IMPRESSION
1. **Right-sided cardiac chamber dilatation, involving predominantly the RA/RV [± main pulmonary artery].**
2. The pattern is most consistent with **[volume overload / pressure overload / ventricular disproportion / indeterminate mechanism]**.
3. **No definite structural cause identified / findings suggest [specific diagnosis].**
4. No definite evidence of significant Ebstein anomaly, major tricuspid dysplasia, TAPVC, major pulmonary venous obstruction, critical pulmonary stenosis/atresia, or major left-sided obstructive lesion on this examination.
5. Recommend **serial fetal echocardiographic follow-up**, particularly if the right-sided dilatation is progressive or associated with TR, abnormal venous Doppler, ventricular dysfunction, hydrops, or suspected pulmonary venous abnormality.
**Note:** Pulmonary venous anatomy, particularly isolated PAPVC, may be difficult to completely exclude prenatally when visualization is limited.
### Important reporting principle
I would **not** write simply *“Right chambers dilated—probably normal fetal variation.”* If the enlargement is definite, the report should document **the mechanism being investigated** and specifically state whether the major causes have been excluded.
For an **RA + RV + PA dilated fetus**, my highest-priority exclusion sequence would be:
**TR/Ebstein → pulmonary veins (TAPVC/PAPVC) → AVSD → pulmonary valve/ductus → high-output state → rhythm → left-sided obstruction/ventricular disproportion.**
